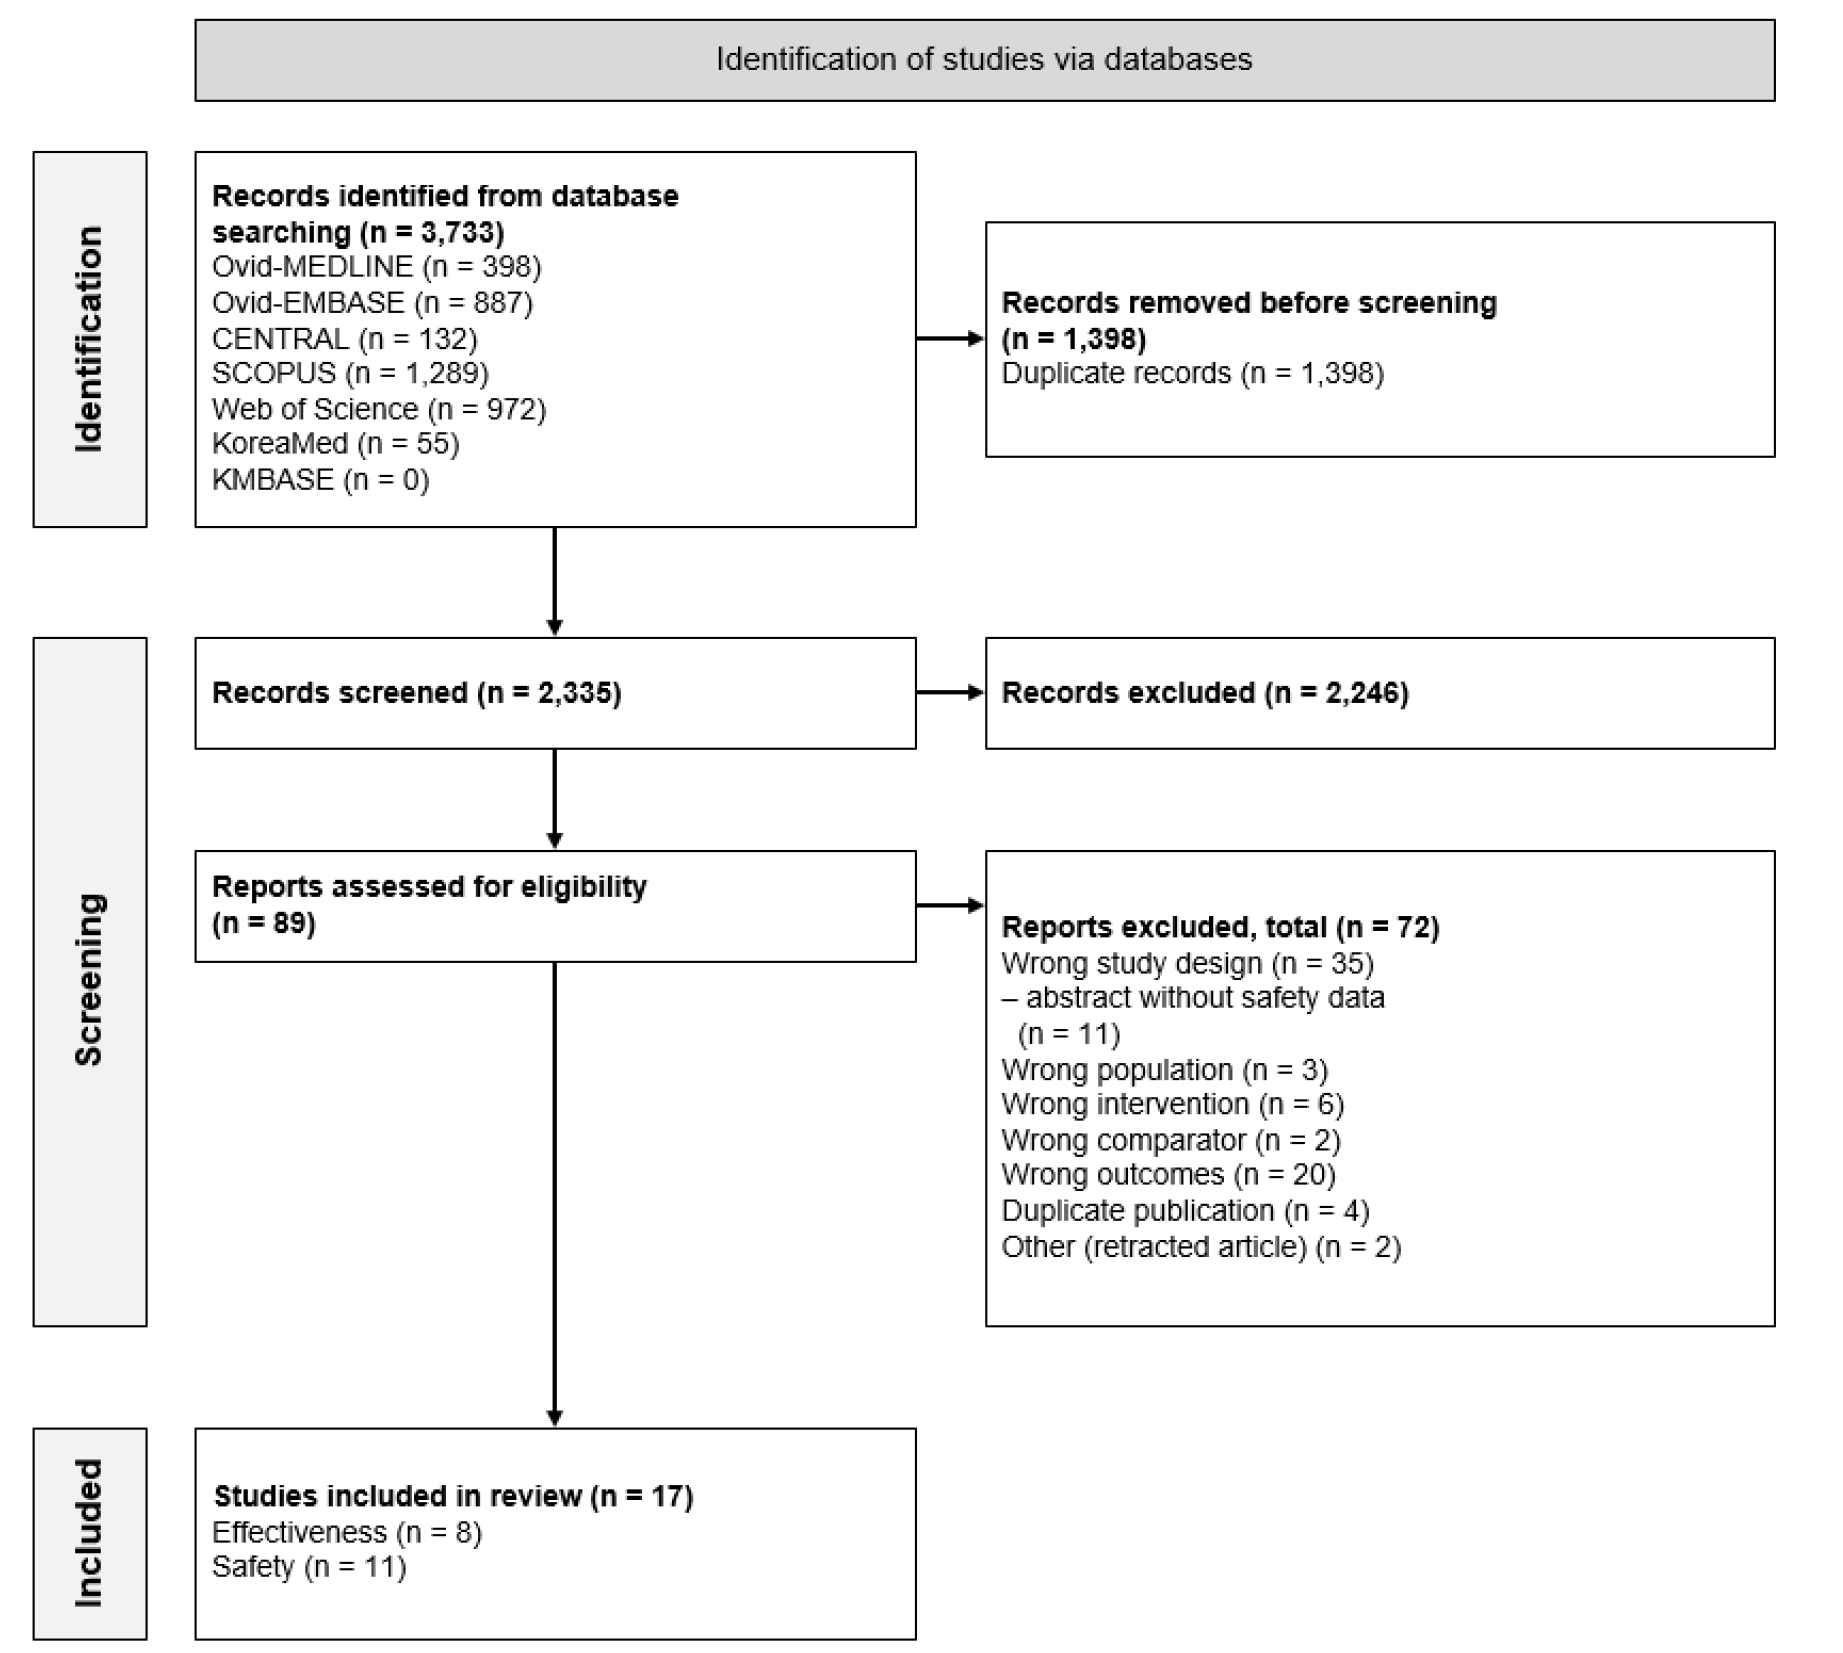
Intravenous intralipid is widely used for women with recurrent reproductive failure —including recurrent pregnancy loss (RPL), recurrent implantation failure (RIF), and repeated IVF failure—despite limited evidence. This systematic review evaluated the effectiveness and safety of intralipid infusion in this population. We searched seven electronic databases from inception to April 14, 2025. RCTs and non-randomized comparative studies (NRCSs) were included for effectiveness analysis; case series and reports for safety. Two reviewers independently screened and extracted data. Risk of bias was assessed using RoB 2.0 and RoBANS 2.0. Meta-analyses used a random-effects model (risk ratios [RR] with 95% CI). Evidence certainty was assessed using GRADE. Seventeen studies were included (8 effectiveness, 11 safety). Pooled RCT data showed intralipid significantly improved clinical pregnancy rate vs. no treatment (RR 2.31, 95% CI 1.42–3.74; I² = 0%; GRADE certainty: low); this effect was not observed in the pooled NRS data for live birth rate or clinical pregnancy rate, and one large NRCS reported a significantly higher miscarriage rate in the intralipid group (RR 1.12, 95% CI 1.04–1.20). No significant differences were observed vs. IVIG or steroids. Serious adverse events were rare. GRADE certainty was very low to low across all outcomes. Current evidence does not support the routine use of intralipid in women with recurrent reproductive failure. While pooled RCT data suggest a potential benefit in clinical pregnancy rate, evidence certainty is low, and this benefit was not observed in the pooled NRS data. Adequately powered RCTs with standardized protocols and live birth rate as the primary endpoint are needed.
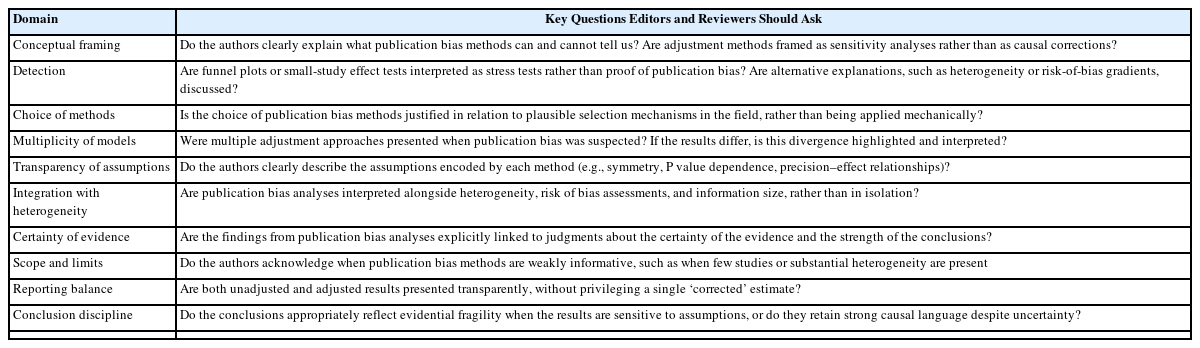
Publication bias is a fundamental threat to the validity of systematic reviews and meta-analyses in clinical medicine. Yet current practice often reduces its assessment to the mechanical application of funnel plots, asymmetry tests, or single adjustment procedures, with limited attention to the underlying assumptions, alternative explanations, or implications for evidence certainty. This narrative methodological article reframes publication bias assessment as an interpretive and editorial responsibility rather than a purely technical problem. We examine what commonly used methods can and cannot reliably support. Detection tools function as nonspecific stress tests that identify deviations from simplified models; they do not diagnose selective publication but highlight situations in which the underlying assumptions require closer inspection. Adjustment approaches, including trim-and-fill, selection models, and regression-based methods, generate hypothetical estimates under unverifiable assumptions**, and therefore provide** sensitivity analyses rather than corrections that recover the true underlying effect. Divergence across adjustment methods is particularly informative, signaling inferential fragility rather than analytical failure. We identify five recurring misinterpretations encountered in peer review: equating asymmetry with proof of publication bias; privileging bias-adjusted estimates as inherently more credible; relying on a single adjustment method without examining assumption dependence; ignoring the plausibility of adjustment direction and magnitude; and overlooking implications for certainty of evidence. Editors and reviewers should prioritize transparency of assumptions, seriously consider alternative explanations, and calibrate conclusions proportionately. Viewing publication bias assessment as an interpretive responsibility rather than a methodological checklist promotes more disciplined inference and strengthens trust in clinical evidence synthesis.
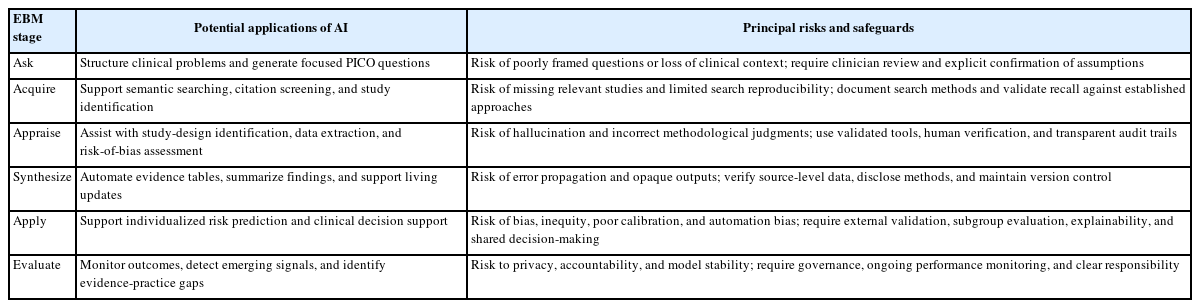
Evidence-based medicine (EBM) has transformed clinical decision-making by integrating the best available research evidence with clinical expertise and patients’ values and preferences. Over the past three decades, EBM has evolved from the critical appraisal of individual studies into a broader framework encompassing evidence synthesis, clinical practice guidelines, assessment of evidence certainty, research transparency, and shared decision-making. Despite these advances, contemporary EBM faces important challenges, including the rapidly increasing volume of research, delays in evidence synthesis and implementation, limited applicability of randomized controlled trials to heterogeneous real-world populations, and difficulties in individualizing population-level evidence. Emerging approaches—including real-world evidence, living evidence, learning health systems, precision medicine, and artificial intelligence (AI)—offer opportunities to address these limitations. Together, these approaches may enable a transition from static to continuously updated evidence, from population-average to more personalized evidence, and from a linear evidence pipeline to a learning evidence ecosystem in which clinical practice both uses and generates evidence. AI may further accelerate evidence retrieval, synthesis, updating, and individualized decision support, while introducing challenges related to reliability, bias, transparency, reproducibility, and accountability. Next-generation EBM should therefore be conceptualized not as a replacement for traditional EBM but as its evolution into a digitally connected, continuously learning evidence ecosystem. In the AI era, the foundational principles of EBM—source verification, critical appraisal, uncertainty assessment, integration of patient preferences, and accountable human judgment—will become increasingly important.
Background Modifiable risk factors account for a substantial proportion of dementia cases and represent important targets for prevention. However, previous studies have often focused on a limited range of risk factors and have rarely examined whether their associations with dementia differ according to sex and age at onset.
Objectives: To investigate sex- and age-specific associations between modifiable risk factors and incident Alzheimer's disease dementia using a nationwide population-based cohort in South Korea.
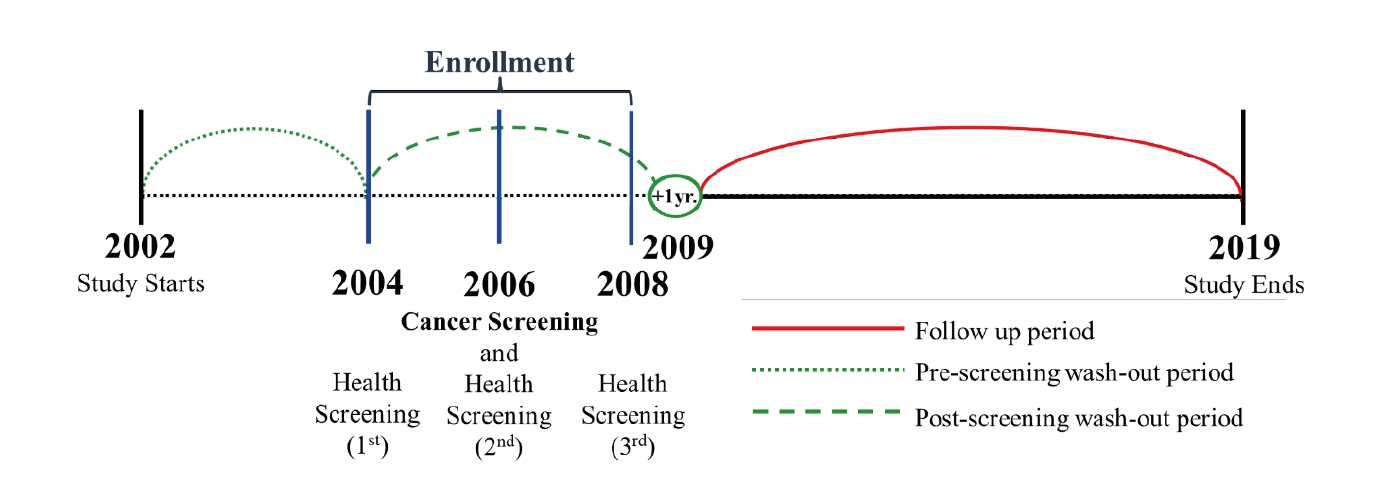
Methods We conducted a retrospective cohort study using the National Health Information Database of the Korean National Health Insurance Service. Among individuals who participated in the National Cancer Screening Program in 2006 and underwent general health examinations in 2004, 2006, and 2008, 599,306 adults aged 40–79 years were included. Participants were followed from 2010 to 2019 after applying pre- and post-screening washout periods. Incident Alzheimer's disease dementia was defined using ICD-10 codes F00 or G30. Cox proportional hazards regression models were used to estimate hazard ratios (HRs) and 95% confidence intervals (CIs). Analyses were stratified by sex and age group to distinguish early-onset Alzheimer's disease dementia (EOAD) and late-onset Alzheimer's disease dementia (LOAD). During the 10-year follow-up period, dementia risk profiles differed substantially according to sex and age at onset. Lower educational attainment was consistently associated with increased dementia risk across all groups. Current smoking and physical inactivity were significant risk factors for dementia in both sexes, whereas underweight status was associated with an increased risk of LOAD. Among chronic conditions, diabetes, hypertension, and depression elevated dementia risk, with depression demonstrating the strongest association, particularly for EOAD (males: HR = 3.61, 95% CI: 2.63–4.96; females: HR = 1.83, 95% CI: 1.46–2.29). Sensory and functional impairments, including hearing loss, visual loss, physical disability, and traumatic brain injury, were also associated with increased dementia risk, although the magnitude and significance of these associations varied by sex and age group. The predictive performance of the models was acceptable, with C-statistics ranging from 0.6784 to 0.7803.
Conclusions The associations between modifiable risk factors and incident Alzheimer's disease dementia exhibited distinct sex- and age-specific patterns. These findings highlight the importance of tailored dementia prevention strategies that account for differences in demographic characteristics and risk factor profiles. Targeted interventions addressing modifiable risk factors may contribute to reducing the future burden of dementia at both individual and population levels.
Background The COVID-19 pandemic triggered extensive global research, leading to an unprecedented surge in both peer-reviewed publications and preprints. Despite their widespread use, the implications of preprints for global diversity in scientific communication remain underexplored. This study evaluates how preprints influenced regional diversity in COVID-19 research by analyzing international collaboration networks, social media engagement, and citation patterns compared to peer-reviewed publications.
Methods We conducted a comparative analysis of COVID-19-related peer-reviewed publications indexed in SCOPUS and preprints from MedRxiv (December 2019–November 2022). Regional diversity was evaluated using bibliometric metrics stratified by World Bank income classifications and geographic regions. International collaboration was quantified using network analysis metrics, while publication, dissemination, and social media engagement were assessed through relative ratios. Social media engagement was measured by quoted posts on X (formerly Twitter). Citation counts were compared between articles with preprint history versus those published directly in journals.
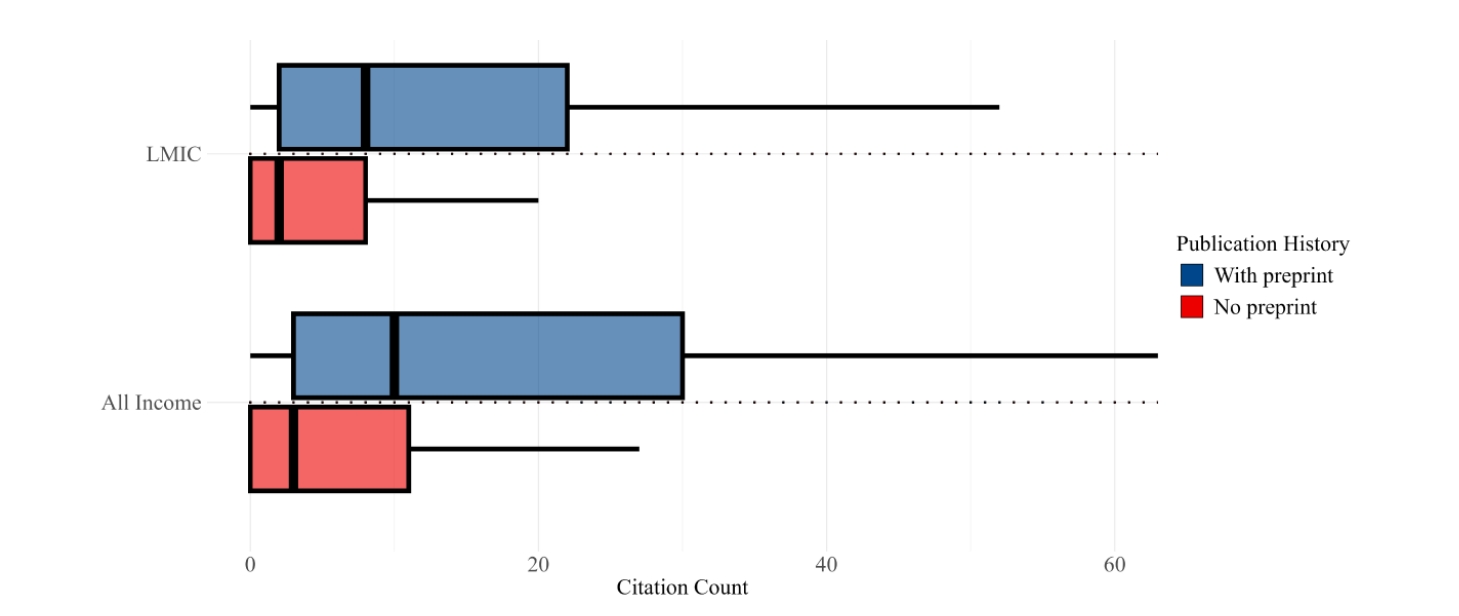
Results Authors from Sub-Saharan Africa, Latin America, and the Caribbean showed 3.9–4.5 times higher eigenvector centrality in preprints than in peer-reviewed papers, indicating greater integration into global research networks through preprint platforms. Low-income countries showed higher representation in preprints (P<0.001). Although overall engagement on X was similar for both formats, preprints exhibited higher relative ratios of quoted posts across all income groups. Peer-reviewed articles with preprint history received more citations (median=10, 25th-75th percentiles: 3–30) than those without (median=3, 25th-75th percentiles: 0–11, P<0.001), especially from low- and middle-income countries.
Conclusions Preprints significantly advanced regional diversity in scientific communication during the COVID-19 pandemic. Preprints enhanced international collaboration networks, particularly benefiting researchers from lower-income regions, facilitated broader social media engagement across all income groups, and conferred meaningful citation advantages for subsequent peer-reviewed publications. These results suggest that preprints represent an important mechanism for promoting more equitable participation in global scientific discourse.
Background Evidence-based medicine (EBM) is an important element of medical education. However, nationwide data on EBM education in Korean medical schools are limited. This study aimed to describe the organizational structure, content, methods, and assessment of EBM education, together with barriers and support needs, and to explore factors associated with variation across schools.
Methods A 26-item questionnaire was administered to EBM education leaders or course directors at 21 Korean medical schools. Data were analyzed descriptively, and differences by structural and exogenous characteristics were explored using cross-tabulation.
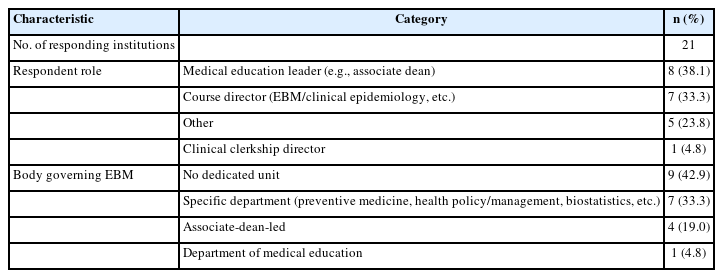
Results Twenty-one of 40 medical schools responded. All responding institutions offered EBM as a mandatory subject, but 42.9% had no dedicated organizing unit. Coverage of classic EBM steps was high (formulating clinical questions: 95.2%; literature searching: 95.2%; critical appraisal: 76.2%), whereas AI-assisted evidence summarization was included in only 19.0%. Only 19.0% reported systematic theory–clinical integration, and 57.1% left bedside EBM to preceptor discretion. Demand for a standardized curriculum guide (90.5%) and faculty development (76.2%) was high, and 100% were willing to use externally developed materials. Variation in key outcomes was associated with organizational governance but was not explained by exogenous structural characteristics such as class size, clinical infrastructure, establishment type, or region.
Conclusions EBM education in Korean medical schools is universally mandatory but uneven in organization, theory–clinical integration, faculty capacity, assessment, and AI integration. These differences appeared to reflect governance more than resource size, suggesting that society-level support should include organizational models alongside standardized curricula, assessment tools, and faculty development.
Background Large language model (LLM)–based tools are increasingly used to automate risk-of-bias assessment of randomized controlled trials with the revised Cochrane tool (RoB 2.0). However, their reproducibility, their accuracy, and their fidelity to the deterministic algorithm mapping signalling-question responses to domain judgments remain unclear.
Methods In a conference workshop, participants used an identical prompt and tool versions to assess one RCT with three configurations and entered each tool’s output verbatim (13, 15, and 10 runs). One experienced reviewer’s assessment served as the reference. For each run we computed run-to-run reproducibility, agreement with the expert, and conformance between the tool’s stated domain judgment and the judgment implied by applying the RoB 2.0 algorithm to that run’s own signalling answers.
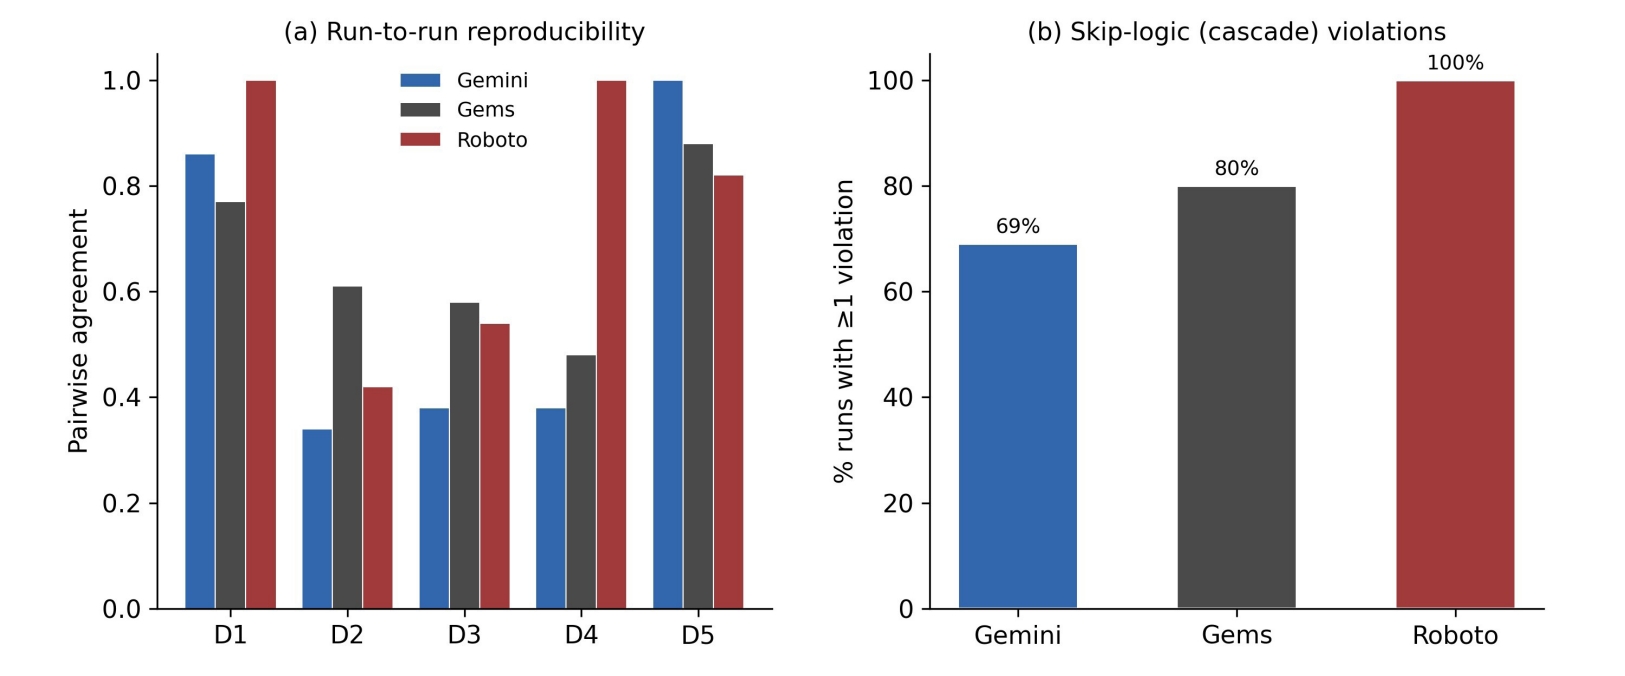
Results All configurations showed substantial run-to-run variability under identical conditions, greatest in the conditionally complex domain 2 (Gemini pairwise agreement 0.34). Expert agreement varied widely across configurations (mean 5–60%), and one configuration systematically under-rated risk. Even in domains with a fully specified algorithm, stated judgments frequently diverged from the value implied by the tool’s own signalling answers (domain 2, mean 42%). Skip-logic violations occurred in 69%, 80%, and 100% of runs. Recomputing domain judgments from the signalling answers improved expert agreement for the general-purpose configurations.
Conclusion LLM-based RoB 2.0 assessments exhibited variability and errors. Whatever tool is adopted, its characteristics and variability must be recognized. Having the tool perform only atomic (single) judgments while delegating aggregation to the algorithm, together with human review, may improve accuracy.
Background Patient values and preferences are important in clinical practice guideline development, but responses indicating reliance on physician judgment may be difficult to interpret. We examined whether such reliance can coexist with explicit preferences about treatment outcomes and trade-offs.
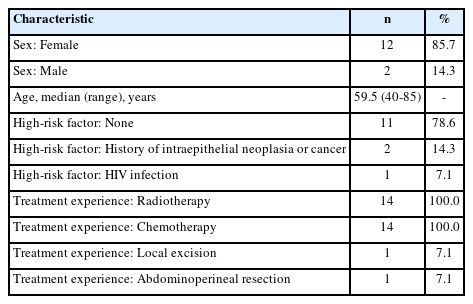
Methods We conducted an exploratory secondary analysis of a 22-item cross-sectional survey completed by 14 adults with anal cancer recruited from four hospitals during guideline development. The survey assessed decision-making participation, responses to specific clinical scenarios, rankings of six treatment goals, and treatment-acceptance thresholds. Ten scenario items included the option “I would follow my treating physician’s judgment.” Analyses were descriptive and emphasized within-participant response patterns.
Results Ten participants (71.4%) generally preferred shared decision-making, yet 11 selected physician judgment in at least one scenario. All 11 completed a full ranking of treatment goals, and 9 completed both trade-off threshold items. Among seven participants who relied on physician judgment for salvage treatment, all completed the ranking and six completed both thresholds; five required at least a 20% survival improvement to accept surgery resulting in a permanent stoma. Although permanent stoma ranked fourth among six goals overall, 11 of 13 respondents required at least a 20% survival improvement to accept such surgery.
Conclusions Reliance on physician judgment did not necessarily indicate an absence of patient preferences. Guideline-related preference studies should distinguish preferences for the decision process, general priorities among outcomes, and context-specific benefit-risk trade-offs. Responses indicating reliance on physician judgment should not automatically be treated as “no preference” or missing information.
Background Leigh syndrome is a mitochondrial disorder in which impaired oxidative phosphorylation causes progressive neurologic damage. Brainstem lesions may cause central hypoventilation, apnea, and recurrent pulmonary infection, increasing perioperative risk.
Case We describe a patient with Leigh syndrome who had chronic central respiratory dysfunction, recurrent pneumonia, and a recent intensive care admission for sepsis and who subsequently underwent tracheostomy under general anesthesia. Anesthesia was induced and maintained with remimazolam and remifentanil. Hemodynamic parameters remained acceptable neuromuscular recovery, spontaneous ventilation remained inadequate, and the patient was returned to the intensive care unit with ventilatory support.
Conclusion In mitochondrial disease, propofol warrants careful consideration because of concerns regarding mitochondrial effects and propofol infusion syndrome. Remimazolam was selected based on severe respiratory vulnerability, recent multiorgan illness, and the anticipated need for postoperative ventilatory support, rather than as evidence of superiority over other agents.
Background Intramural esophageal dissection (IED) is a rare esophageal injury that is usually managed conservatively. However, the optimal treatment for complicated IED associated with infection or mediastinal abscess remains unclear.
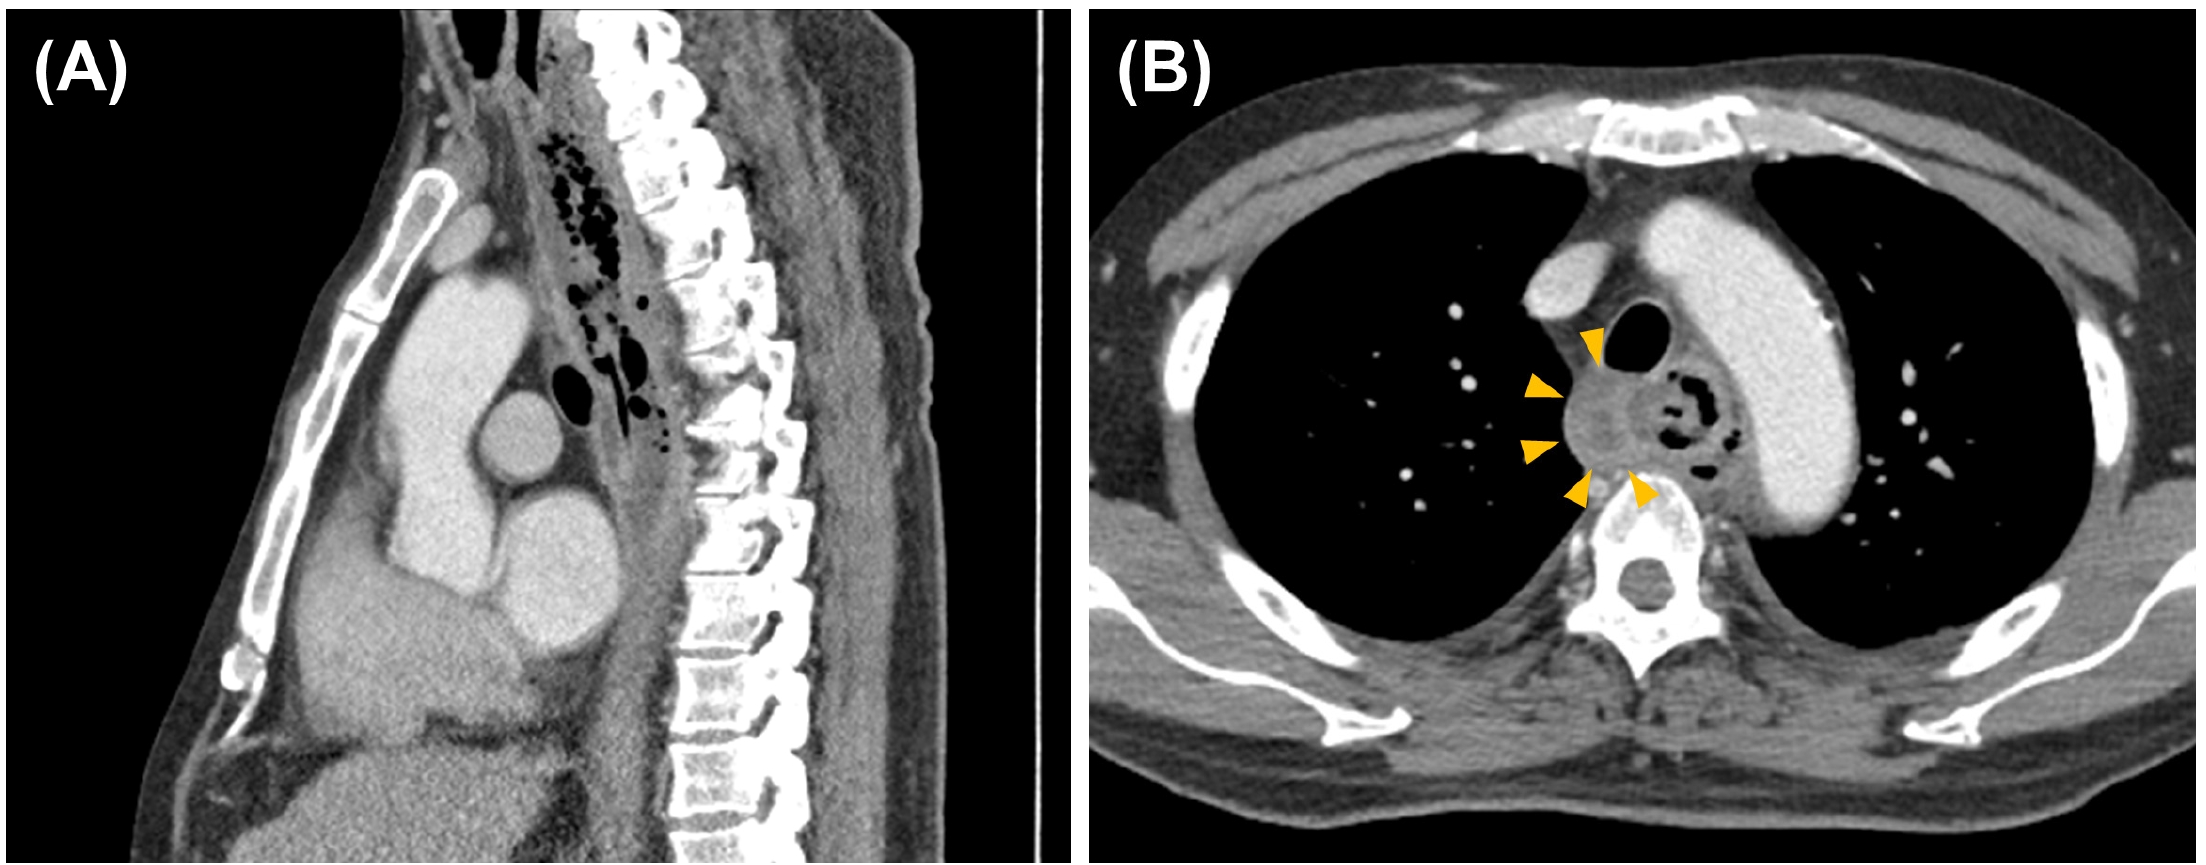
Case A 57-year-old man with decompensated liver cirrhosis presented with chest pain, odynophagia, and fever. Chest computed tomography revealed IED complicated by mediastinal abscess. Despite conservative management and thoracoscopic drainage, persistent fever suggested inadequate drainage of the infected false lumen. Endoscopic internal drainage was performed by longitudinal mucosal incision, followed by enteral nutritional support via feeding jejunostomy. The patient recovered without major surgery. Six-month follow-up endoscopy demonstrated complete healing of the false lumen with restoration of a single esophageal lumen.
Conclusions Endoscopic internal drainage may be a feasible organ-preserving treatment option for selected patients with infected IED when adequate drainage cannot be achieved by conservative management or surgical drainage alone.




 First
 Prev



