Background Patient values and preferences are important in clinical practice guideline development, but responses indicating reliance on physician judgment may be difficult to interpret. We examined whether such reliance can coexist with explicit preferences about treatment outcomes and trade-offs.
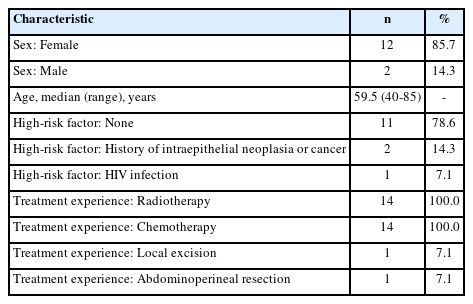
Methods We conducted an exploratory secondary analysis of a 22-item cross-sectional survey completed by 14 adults with anal cancer recruited from four hospitals during guideline development. The survey assessed decision-making participation, responses to specific clinical scenarios, rankings of six treatment goals, and treatment-acceptance thresholds. Ten scenario items included the option “I would follow my treating physician’s judgment.” Analyses were descriptive and emphasized within-participant response patterns.
Results Ten participants (71.4%) generally preferred shared decision-making, yet 11 selected physician judgment in at least one scenario. All 11 completed a full ranking of treatment goals, and 9 completed both trade-off threshold items. Among seven participants who relied on physician judgment for salvage treatment, all completed the ranking and six completed both thresholds; five required at least a 20% survival improvement to accept surgery resulting in a permanent stoma. Although permanent stoma ranked fourth among six goals overall, 11 of 13 respondents required at least a 20% survival improvement to accept such surgery.
Conclusions Reliance on physician judgment did not necessarily indicate an absence of patient preferences. Guideline-related preference studies should distinguish preferences for the decision process, general priorities among outcomes, and context-specific benefit-risk trade-offs. Responses indicating reliance on physician judgment should not automatically be treated as “no preference” or missing information.
Background Large language model (LLM)–based tools are increasingly used to automate risk-of-bias assessment of randomized controlled trials with the revised Cochrane tool (RoB 2.0). However, their reproducibility, their accuracy, and their fidelity to the deterministic algorithm mapping signalling-question responses to domain judgments remain unclear.
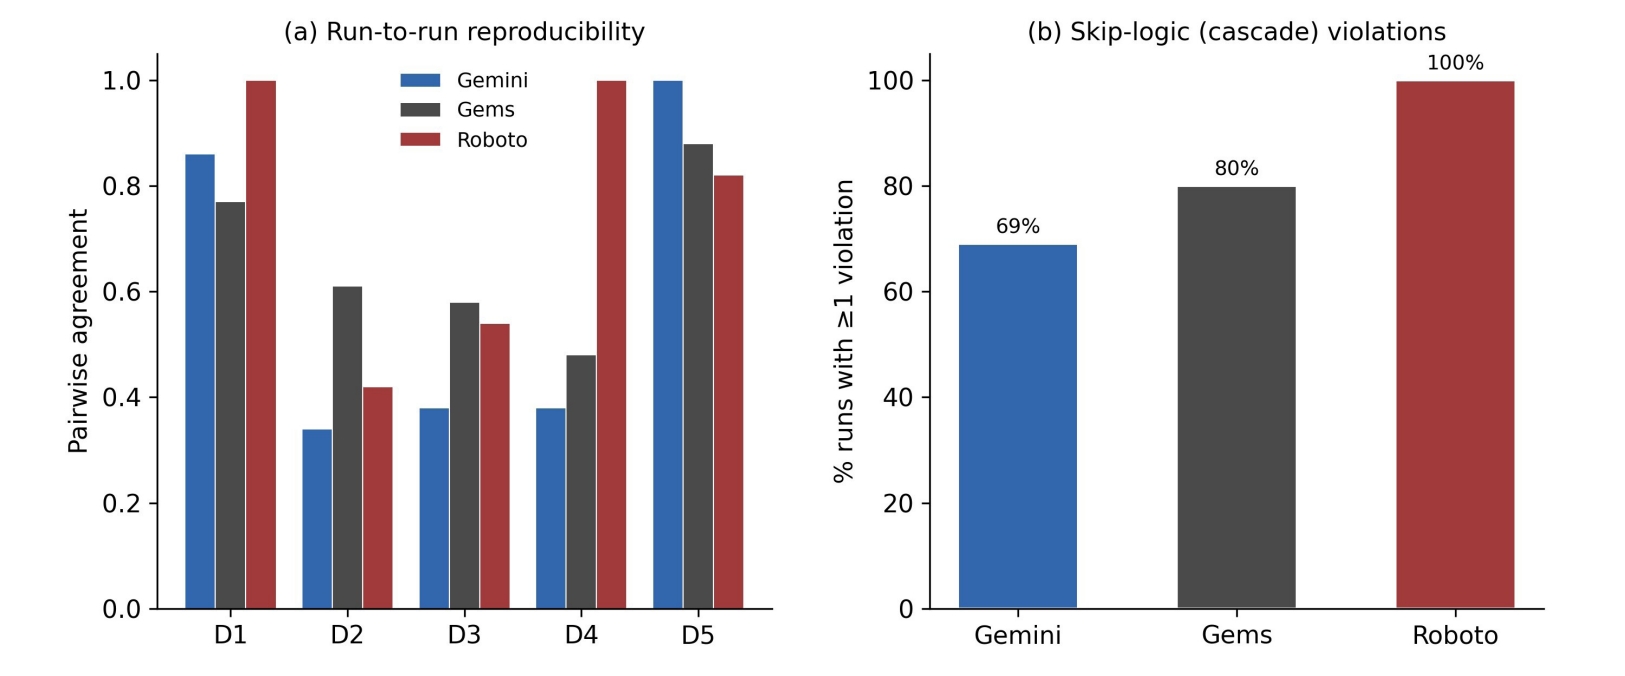
Methods In a conference workshop, participants used an identical prompt and tool versions to assess one RCT with three configurations and entered each tool’s output verbatim (13, 15, and 10 runs). One experienced reviewer’s assessment served as the reference. For each run we computed run-to-run reproducibility, agreement with the expert, and conformance between the tool’s stated domain judgment and the judgment implied by applying the RoB 2.0 algorithm to that run’s own signalling answers.
Results All configurations showed substantial run-to-run variability under identical conditions, greatest in the conditionally complex domain 2 (Gemini pairwise agreement 0.34). Expert agreement varied widely across configurations (mean 5–60%), and one configuration systematically under-rated risk. Even in domains with a fully specified algorithm, stated judgments frequently diverged from the value implied by the tool’s own signalling answers (domain 2, mean 42%). Skip-logic violations occurred in 69%, 80%, and 100% of runs. Recomputing domain judgments from the signalling answers improved expert agreement for the general-purpose configurations.
Conclusion LLM-based RoB 2.0 assessments exhibited variability and errors. Whatever tool is adopted, its characteristics and variability must be recognized. Having the tool perform only atomic (single) judgments while delegating aggregation to the algorithm, together with human review, may improve accuracy.
Background Evidence-based medicine (EBM) is an important element of medical education. However, nationwide data on EBM education in Korean medical schools are limited. This study aimed to describe the organizational structure, content, methods, and assessment of EBM education, together with barriers and support needs, and to explore factors associated with variation across schools.
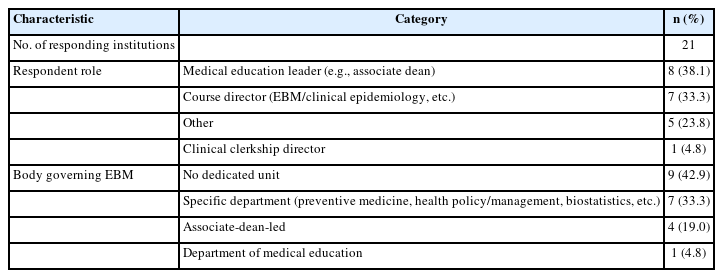
Methods A 26-item questionnaire was administered to EBM education leaders or course directors at 21 Korean medical schools. Data were analyzed descriptively, and differences by structural and exogenous characteristics were explored using cross-tabulation.
Results Twenty-one of 40 medical schools responded. All responding institutions offered EBM as a mandatory subject, but 42.9% had no dedicated organizing unit. Coverage of classic EBM steps was high (formulating clinical questions: 95.2%; literature searching: 95.2%; critical appraisal: 76.2%), whereas AI-assisted evidence summarization was included in only 19.0%. Only 19.0% reported systematic theory–clinical integration, and 57.1% left bedside EBM to preceptor discretion. Demand for a standardized curriculum guide (90.5%) and faculty development (76.2%) was high, and 100% were willing to use externally developed materials. Variation in key outcomes was associated with organizational governance but was not explained by exogenous structural characteristics such as class size, clinical infrastructure, establishment type, or region.
Conclusions EBM education in Korean medical schools is universally mandatory but uneven in organization, theory–clinical integration, faculty capacity, assessment, and AI integration. These differences appeared to reflect governance more than resource size, suggesting that society-level support should include organizational models alongside standardized curricula, assessment tools, and faculty development.
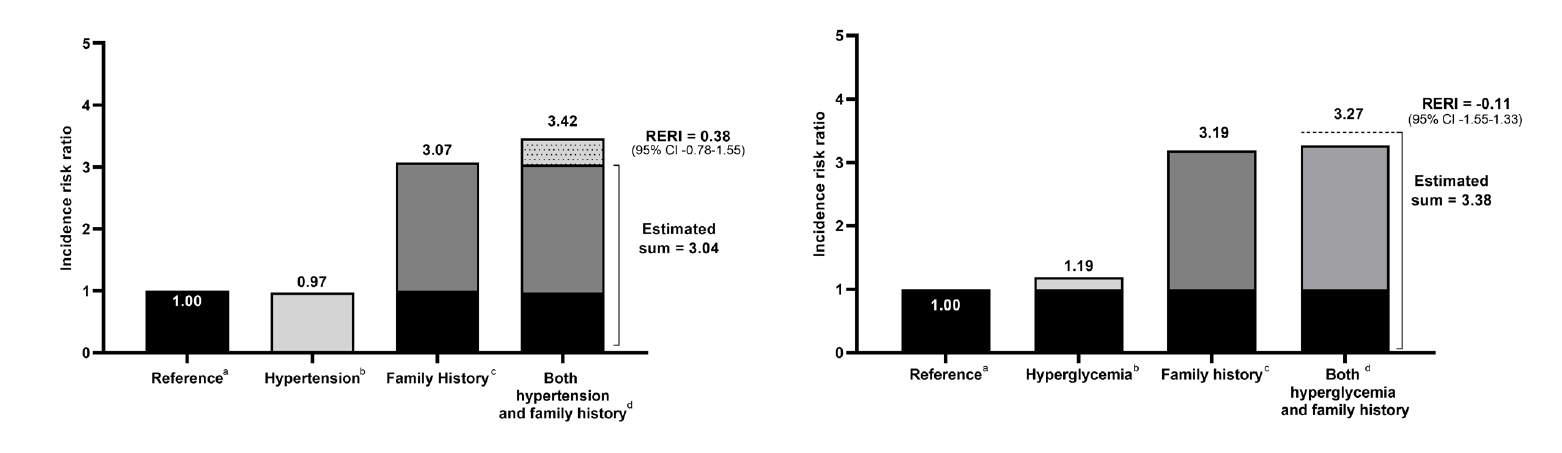
Although there is a genetic component to primary open-angle glaucoma (POAG) susceptibility, few studies have investigated interactions between genetic and environmental factors. We aimed to quantify the familial risk of POAG and estimate disease risk among individuals with a positive family history and either hypertension or hyperglycemia, as well as assess their interactions. Using the National Health Insurance database, which includes information on familial relationships and lifestyle risk factors, we identified 6,217,057 individuals with first-degree relatives (FDRs) from 2002-2018. We calculated familial risk using hazard ratios (HRs) with 95% confidence intervals (CIs) which compare the risk of individuals with and without affected FDRs. Disease risk was estimated among individuals with both a positive family history and hypertension or hyperglycemia, and interactions were assessed on an additive scale. Individuals with an affected parent had a 3.13-fold (95% CI 2.74 –3.58) increased risk of disease compared to those with unaffected parents. Individuals with affected father, mother, or both affected parents showed HRs (95% CI) of 3.50 (2.86 –4.30), 2.87 (2.41 –3.44) and 4.88 (1.83 –12.98), respectively. Familial risk adjusted for lifestyle factors decreased slightly (HR 3.14), suggesting that genetic component is the predominant driver in the familial aggregation. Individuals with a positive family history and either hypertension or hyperglycemia had a markedly elevated risk of disease, with HRs of 3.42 (95% CI 2.49 –4.69) and 3.27 (95% CI 2.15 –4.97), respectively. Hypertensive or hyperglycemic individuals with a positive family history may be considered a high-risk group and glaucoma screening may be considered.



 First
 Prev



